

Take Control of the Case
Diagnosis, Imaging, and Appliance Selection
Hands-On Dental Course | Level 3
Understand exactly how the patient got here, and know exactly what to do about it.
Level 3 goes deeper into the diagnosis itself. Before an appliance is chosen, the whole patient has to be read: not one finding at a time, but every sign the mouth and the imaging carry, assembled into an account of how the patient arrived at this condition. The appliance is the last decision in that process, not the first.
You will interpret vertical dimension, over-eruption, wear facets, abfractions, and gingival recession as related evidence of the same functional history. You will learn what the bone, the arch form, and the panoramic radiograph indicate, when a CBCT or an MRI is warranted, and what each of those images does and does not show. From that complete read you will determine the etiology, define what the appliance must correct, and select the appliance accordingly. Level 3 is the diagnostic foundation for the orthotic therapy delivered and adjusted in Level 4.
Learning objectives
Upon completion, participants will be able to:
Assess vertical dimension and classify it as lost, maintained, or altered, and identify the mechanism behind the change.
Read over-eruption, wear facets, craze lines, abfractions, fractured teeth and restorations, and gingival recession together as evidence of a shared functional history rather than as separate findings.
Interpret what alveolar bone, arch form, and arch size indicate about load, function, and stability.
Interpret the panoramic radiograph and identify the findings that call for advanced imaging.
State the indications for CBCT and MRI, and describe what each modality shows and does not show.
Interpret CBCT findings, including condylar morphology, and determine their effect on the treatment plan.
Construct an etiologic diagnosis that explains how the patient reached the current condition.
Define what the appliance must correct, in terms of vertical dimension, mandibular position, and condylar seat.
Select an appliance on the basis of the diagnosis, and justify the choice against the corrective objective.
Course details
Location: Smiles by Bis
710 Dorval Dr #220, Oakville, ON L6K 3V7
Date: April 9 - 10, 2027
CE Credits: 14
Dentist tuition: $3,995 CAD
Hygienist or assistant: $980
Format: Two-day, in-person course
Course content
-
Level 3 assembles the diagnosis from every available sign at once. A finding read in isolation misleads; the same finding read against the others explains the case. This level teaches you to read the mouth, the bone, and the imaging as a single body of evidence, and to hold the appliance decision until that reading is complete.
-
Vertical dimension is central to both diagnosis and appliance design, and it is frequently misjudged. This module teaches you to assess it, to classify it as lost, maintained, or altered, and to identify the mechanism behind the change. Lost vertical dimension and apparent loss are not the same, and the difference determines what the appliance must restore.
-
Teeth move when the forces on them change. Over-eruption, drifting, and the collapse of an unstable occlusion are signs of that movement. This module teaches you to recognize them and to read what they indicate about the stability of the occlusion and the space available for treatment.
-
These findings are routinely attributed to three separate causes: attrition, abrasion, brushing and clenching. Read together, they often describe a single functional problem. This module teaches you to interpret wear facets, craze lines, abfractions, pattern of chipping, and gingival recession as related evidence of load and parafunction, and to recognize when the conventional single-cause explanation is wrong.This module teaches a second reading of the film. Four findings are covered in detail: condylar form and cortical integrity, vertical symmetry of the condyle–ramus unit, antegonial morphology, and the load signature written into the teeth and alveolar bone. Each is tied to the mechanism that produced it and to the clinical decision it changes.
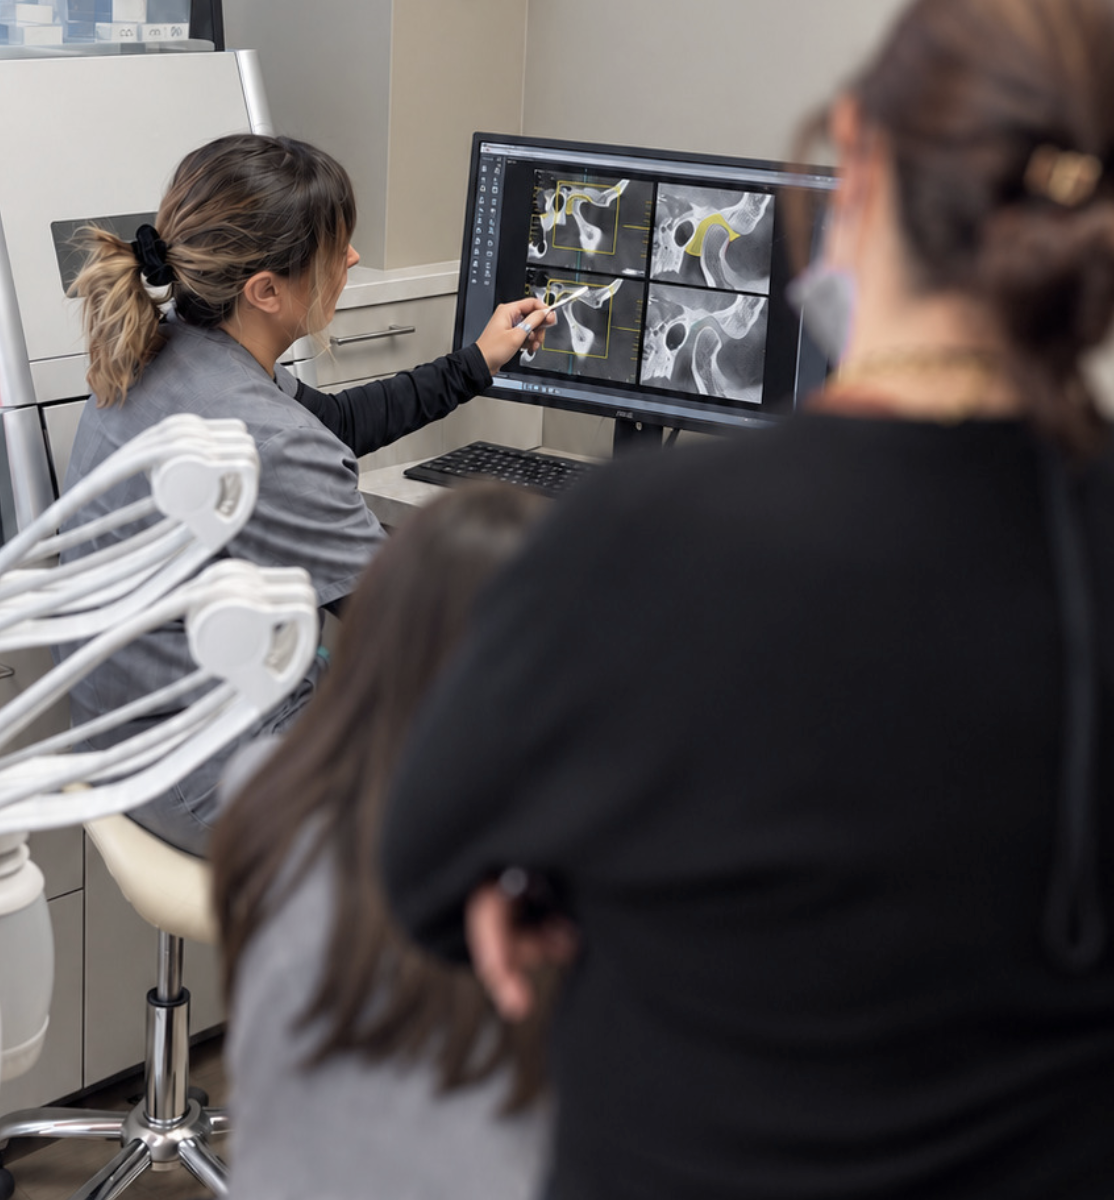
The module also defines the limits of the image. A panoramic radiograph cannot show disc position and cannot establish condylar position or 3-dimensional shape in the fossa. It raises suspicion and directs further imaging. It does not exclude joint disease. Participants learn which findings warrant CBCT, which warrant MRI, and which warrant neither.
-
Bone records the history of load, not only the history of hygiene. This module teaches you to read what alveolar bone morphology and level indicate about function, and what arch shape and size reveal about how the dentition developed and what will constrain treatment.
-
Each imaging modality answers a different question. The panoramic radiograph is a two-dimensional overview and a screening tool, with limits you must know. CBCT provides three-dimensional bony detail, including condylar morphology, but it does not show the disc. MRI shows the soft tissue, including disc position and displacement. This module teaches you when each is indicated, what each does and does not show, and what to do with the findings.The cephalogram is not a routine record. This module defines the specific indications that justify the exposure, and the protocol that must be followed before the image can answer a postural question. Head position is the controlling variable. An image taken with the head positioned by the cephalostat answers skeletal questions and no postural ones, which is the most common error in how these films are taken.
The interpretation covers craniocervical angulation, cervical curvature, hyoid position, posterior airway, and the sagittal and vertical skeletal relationships, and then connects them to the mandible. The mandible has no fixed skeletal support below. It is suspended between the elevator group above and the suprahyoid and infrahyoid groups below, and the hyoid is anchored downward to the shoulder girdle. Head extension and forward head carriage change the length and direction of pull of that lower group and add a posterior and inferior vector on the mandible. Rest position and the path of closure move with it.
-
This module brings the signs and the images together into an account of how the patient reached the current condition: the sequence of events, the current mandibular and condylar position, and what must be corrected. This is the etiologic diagnosis, and it is what the appliance choice depends on.
-
The appliance is the last decision, made after the diagnosis is complete, not before. Teeth are the stops that set where the mandible closes and where the condyle seats; an appliance replaces those stops. Not every appliance moves the condyle. Some only separate or protect the teeth; some deprogram the muscles; the orthotic is the only device that moves the condyle in the corrective direction, toward the Optimal Physiologic Position the diagnosis defines. This module teaches you to state what the appliance must correct - the vertical, the mandibular position, the condylar seat - and to select the appliance that meets that objective, rather than defaulting to the appliance you already use.
Hands-on practical exercises
Vertical dimension assessment
Mapping wear facets, abfractions, over-eruption, and recession as one picture
Arch form and size evaluation
Panoramic radiograph interpretation
CBCT interpretation, including condylar morphology
Ceph interpretation, including mandible position, and impact on head position and cervical alignment
Imaging-decision exercise: choosing panoramic, CBCT, Ceph, or MRI and defending it
Etiologic diagnosis workshop: constructing how the patient got here
Appliance-selection exercise: matching the appliance to the corrective objective
Your Monday-morning toolkit
Every level ends with a single-page tool you can apply the next working day. It is not a course summary. It is an instrument, built for chairside use by you and your team.
Level 3 - The Appliance Selection Guide.
A one-page decision aid that maps the diagnostic findings, vertical dimension, mandibular and condylar position, joint status, and occlusal stability, to the appliance indicated and the corrective objective it serves. It lets you move from a completed diagnosis to a defensible appliance choice, and to state why that appliance and not another.

Bringing a team member
This course is open to team members. The protocols in this level are taught to be executed by the team, not the dentist alone: records, photography, digital scanning, occlusal analysis, and the setup that supports case presentation. When your team member learns them beside you, the workflow is adopted the week you return, rather than taught secondhand and lost. The most common reason continuing education does not change a practice is that the team never trained on it.
The economics of comprehensive treatment
Level 3 determines the appliance the case requires and the imaging the diagnosis justifies. Both decisions carry a cost when they are made without the full picture. Three drivers follow from the material.
The right appliance, chosen once. An appliance selected without the complete diagnosis may not correct the problem. It is then remade or abandoned, at the patient's expense and yours. A choice made from a full diagnostic read is delivered once, not remade.
Imaging ordered when it changes the plan. Knowing when a CBCT or MRI is indicated, and when it is not, means you neither miss the findings that alter treatment nor add cost that returns nothing. The imaging you take is justified, documented, and used.
Etiology the patient understands supports the largest cases you treat. Orthotic therapy followed by Phase 2 is among the highest-value treatment a general practice delivers. When the patient understands how they arrived at their condition, that treatment is accepted on its merits.
Ready to connect the findings and take control of the case?
Level 3 brings the clinical signs, imaging, vertical dimension, joint findings, and functional history together so you can understand how the patient got here, what needs to be corrected, and which treatment approach is appropriate.
New to the Hands-On Series? Start with Level 1 to build the diagnostic foundation first.
Bridge to Level 4
Level 3 completes the diagnosis and selects the appliance. Level 4 delivers and adjusts the orthotic - Phase 1 therapy - and manages the movement of the mandible to the corrected position. The pathway then continues to Phase 2, the finalization that follows orthotic therapy, and to the management of complex cases.
Have a question before registering?
Not sure which level is right for you, what to expect, or whether you should bring a team member? Send us your question and our team will get back to you.

About the instructor
Dr. Agatha Bis has spent nearly 30 years treating complex cases in private practice with a clinical focus on TMJ disorders, occlusion, restorative dentistry, and the systems that make treatment more predictable. She is also the founder of TMJ Whisperer Academy, an educational platform built for dentists who want to understand cases more clearly, diagnose with more confidence, and practice with more control.